



Table of Contents
- Quick Summary
- What Is Epilepsy Surgery?
- Who Is a Candidate for Epilepsy Surgery?
- Can Children Have Epilepsy Surgery?
- Which Doctor Evaluates a Patient for Epilepsy Surgery?
- Is Epilepsy Surgery Available in India?
- What Tests Are Done Before Epilepsy Surgery?
- How Is Epilepsy Surgery Planned?
- How Is Epilepsy Surgery Performed?
- What Are the Types of Epilepsy Surgery?
- What Is the Success Rate of Epilepsy Surgery in India?
- Is Epilepsy Surgery Safe?
- What Is the Recovery Time After Epilepsy Surgery?
- Will I Need Anti-Seizure Medication After Epilepsy Surgery?
- When May Epilepsy Surgery Not Be Recommended?
- What Should You Ask Before Epilepsy Surgery?
- Conclusion
- FAQs
Quick Summary
- Epilepsy surgery may be considered when seizures remain uncontrolled despite appropriate anti-seizure medicines, particularly when testing identifies a seizure focus that can be treated safely.
- Before surgery, an epilepsy centre usually performs a detailed presurgical evaluation, which may include video EEG, high-resolution MRI, neuropsychological testing and, in selected cases, PET, SPECT or intracranial EEG.
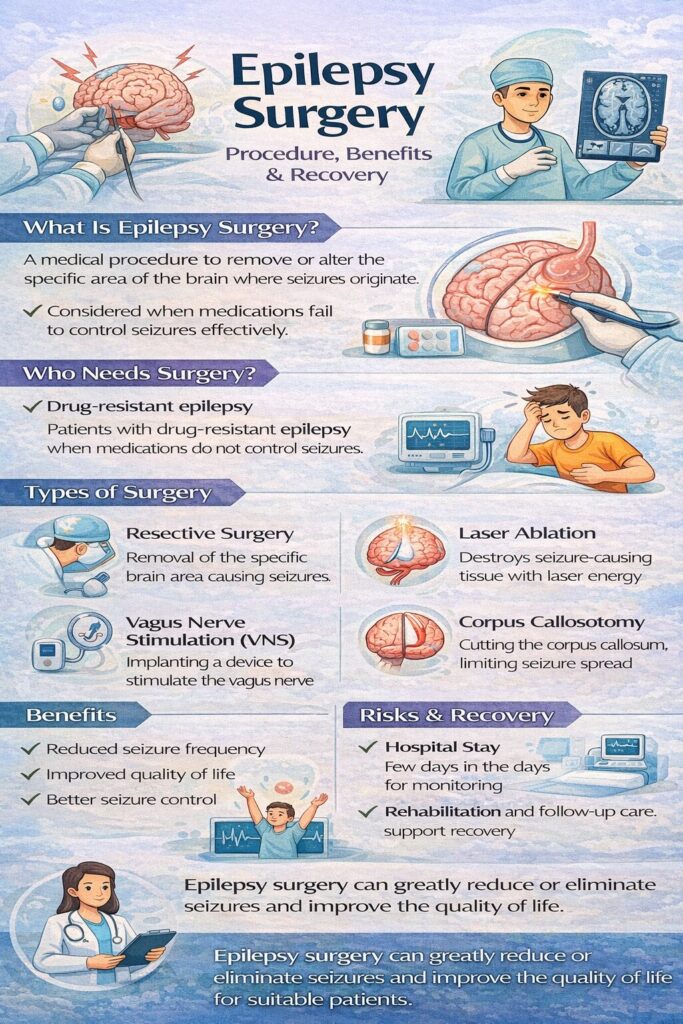
- The types of epilepsy surgery include resection, ablation, disconnection procedures and neuromodulation. The appropriate option depends on where seizures begin and whether that area can be safely treated.
- Epilepsy surgery can provide long-term seizure control in appropriately selected patients, but there is no single success rate for everyone. Outcomes vary by epilepsy type, procedure, seizure focus, and other factors.
- Indian studies have reported favourable outcomes in selected adult and paediatric surgical populations, but these study results should not be interpreted as a universal success rate.
- Recovery depends on the procedure and individual circumstances. Some people continue anti-seizure medicines after surgery, even when seizures are well controlled.
What Is Epilepsy Surgery?
Epilepsy surgery is a group of procedures used to reduce or stop seizures when medicines do not adequately control epilepsy. It is most often considered for drug-resistant epilepsy, particularly when doctors can identify the brain region responsible for seizures and determine that treating it can be done without causing an unacceptable neurological deficit.
The aim is not always to remove part of the brain. Depending on the type and location of epilepsy, treatment may involve removing the seizure-producing tissue, destroying it without a traditional open resection, disconnecting pathways through which seizures spread, or using a device to reduce seizure activity.
The decision is therefore based on a detailed evaluation rather than the diagnosis of epilepsy alone.
Who Is a Candidate for Epilepsy Surgery?
A person may be considered for epilepsy surgery when seizures continue despite appropriate treatment with anti-seizure medicines and investigations suggest that surgery could provide meaningful seizure control with an acceptable level of risk.
The International League Against Epilepsy (ILAE) recommends that people with drug-resistant epilepsy should be offered a referral for surgical evaluation as soon as drug resistance is established, rather than waiting for years of uncontrolled seizures.
Drug-resistant epilepsy generally refers to continued seizures despite adequate trials of two appropriately selected, tolerated, and used anti-seizure medicines. The ILAE notes that about one-third of people with epilepsy continue to have seizures despite medication, and some people with drug-resistant epilepsy may be candidates for surgery or stimulation-based treatment.
Does Drug-Resistant Epilepsy Mean Surgery Is Necessary?
No. Drug-resistant epilepsy does not automatically mean that a person will undergo surgery.
It means that a specialist epilepsy team should consider whether a surgical evaluation is appropriate.
The presurgical evaluation looks at questions such as:
- Where do the seizures begin?
- Is there a clearly identifiable seizure focus?
- Can that area be removed or treated safely?
- Is the seizure-producing region close to areas responsible for speech, movement, vision, or memory?
- Would another treatment, such as ablation or neuromodulation, be more appropriate?
- Are the test results sufficiently consistent to support a treatment plan?
Some people are found to be good candidates for surgery intended to achieve long-term seizure freedom. Others may be better suited to a procedure intended to reduce seizure frequency or severity, while some may not be suitable for surgery at all.
Can Children Have Epilepsy Surgery?
Yes. Children can undergo epilepsy surgery when a comprehensive evaluation shows that surgery is appropriate.
In children with drug-resistant epilepsy, prolonged uncontrolled seizures can affect development, learning, behaviour and quality of life. This is one reason early referral to a specialist epilepsy centre can be important rather than delaying evaluation until adolescence or adulthood.
India also has clinical evidence supporting surgery in appropriately selected children. A study of 242 children treated at a tertiary epilepsy centre in India reported an 81.38% Engel Class I outcome after definitive surgery, with median follow-up of 32 months.
Engel Class I is a commonly used epilepsy-surgery outcome category indicating little to no disabling seizures. The reported outcome differed according to the type of surgery, reaching 92.3% for temporal-lobe procedures, 87.17% for hemispheric procedures, and 75.32% for extratemporal procedures.
These figures describe a selected surgical population and should not be interpreted as the expected outcome for every child with epilepsy.
Which Doctor Evaluates a Patient for Epilepsy Surgery?
Epilepsy surgery is usually evaluated by a multidisciplinary epilepsy team, rather than by a surgeon alone.
Depending on the patient’s needs, the team may include:
- Epileptologist or neurologist: a doctor specialising in epilepsy and seizure disorders.
- Neurosurgeon: a surgeon specialising in operations involving the brain, spinal cord and nervous system, with epilepsy-surgery expertise where applicable.
- Neuroradiologist: a doctor who specialises in interpreting brain and nervous-system imaging such as MRI.
- Neuropsychologist: a specialist who assesses cognitive functions such as memory, attention, language and reasoning.
- Psychiatrist or neuropsychiatrist: a specialist who can assess psychiatric, behavioural and cognitive factors when needed.
- EEG specialists: professionals involved in recording and interpreting electrical activity in the brain.
- Nuclear medicine or functional imaging specialists: doctors involved in specialised scans such as PET and SPECT.
- Rehabilitation and allied-health professionals when required.
The purpose of the team is to bring together seizure history, EEG findings, brain imaging, cognitive testing and other investigations before deciding whether and how surgery should be performed.
Also Read: Epilepsy: Causes, Diagnosis, Treatment, & More
Is Epilepsy Surgery Available in India?
Yes. Epilepsy surgery is available in India at specialised epilepsy centres.
India has established epilepsy-surgery programmes involving presurgical evaluation, resective surgery, disconnection procedures and other surgical or neuromodulation approaches.
A 2017 review of epilepsy surgery in India reported that, by July 2016, approximately 7,143 epilepsy surgeries had been performed across 39 centres, with about 734 procedures being performed annually at that time. The authors also highlighted a substantial treatment gap, reporting that only around 2 in 1,000 eligible patients underwent epilepsy surgery. These figures are historical and should not be treated as the current number of Indian centres or procedures.
For a patient considering surgery today, the more important question is not simply whether a hospital performs epilepsy surgery, but whether it has the specialised multidisciplinary evaluation and surgical expertise appropriate for the person’s epilepsy.
What Tests Are Done Before Epilepsy Surgery?
The purpose of presurgical testing is to identify the epileptogenic zone, the brain region believed to be responsible for generating seizures, and determine whether it can be treated safely.
No single test is always sufficient. The evaluation combines information from several investigations, and the exact tests depend on the individual’s epilepsy.
1. Video EEG Monitoring
Long-term video EEG records brain electrical activity alongside the person’s clinical behaviour and symptoms.
EEG, or electroencephalography, is a test that records the brain’s electrical activity using electrodes placed on the scalp.
Video EEG helps doctors determine:
- whether the events are epileptic seizures
- where seizures appear to begin
- what the seizures look like clinically
- whether EEG findings agree with other investigations
Video EEG is a core component of presurgical evaluation.
2. High-Resolution Brain MRI
MRI, or magnetic resonance imaging, uses detailed images of the brain to look for structural abnormalities that may be responsible for seizures, such as:
- Hippocampal sclerosis: scarring or structural damage affecting the hippocampus, a brain region involved in memory and commonly associated with temporal-lobe epilepsy.
- Focal cortical dysplasia: abnormal development of the brain’s outer layer, or cerebral cortex, which can cause seizures.
- Tumours
- Vascular abnormalities
- Scars or other structural lesions
A high-quality epilepsy-protocol MRI can provide information that is particularly important when determining whether a structural lesion corresponds with the seizure focus.
3. Neuropsychological Testing
Neuropsychological assessment evaluates functions such as:
- memory
- attention
- language
- reasoning
- learning
- other aspects of cognitive functioning
It can help doctors understand how epilepsy affects brain function and assess the potential cognitive implications of a proposed operation.
4. PET or SPECT
Functional imaging may be used when MRI or other investigations do not provide enough information.
PET, or positron emission tomography, is an imaging technique that shows patterns of brain metabolism and can help identify areas associated with seizures.
SPECT, or single-photon emission computed tomography, can show changes in blood flow. Ictal SPECT is performed around the time of a seizure and may help identify the region where seizure activity begins.
These investigations are generally used selectively rather than being required for every patient. Indian recommendations describe PET and SPECT as useful in selected drug-resistant epilepsy cases.
5. Functional Mapping
When the seizure focus is close to areas responsible for speech, movement or other important functions, additional testing may be used to map those functions.
Functional mapping identifies brain areas responsible for important abilities such as speech, movement, sensation or memory.
The purpose is to help the surgical team understand what brain tissue can potentially be treated while minimising the risk of significant neurological deficits.
6. Intracranial EEG
If non-invasive investigations do not provide enough information, doctors may consider placing electrodes inside or directly on the brain to record seizure activity more precisely.
Intracranial EEG is an invasive form of EEG in which electrodes are placed within the skull or directly on the brain rather than only on the scalp.
It is not required for every patient. It may be considered when non-invasive findings are inconclusive or contradictory, or when more precise localisation is required for treatment planning.
Plan your treatment finances smarter with the Disease Cost Calculator.
How Is Epilepsy Surgery Planned?
Epilepsy surgery is planned by bringing together the findings from the presurgical evaluation.
Doctors essentially need to answer two questions:
Where are the seizures coming from?
and
Can that area be treated without causing an unacceptable loss of important brain function?
When the EEG, MRI, functional imaging, neuropsychological testing and clinical history point toward the same region, doctors may have greater confidence in the surgical plan. When the results conflict, additional testing may be required.
This is why epilepsy surgery is not based on an MRI scan alone. Presurgical evaluation is a stepwise, multimodal process in which the different investigations are interpreted together.
How Is Epilepsy Surgery Performed?
The exact procedure depends on the type and location of epilepsy.
In some patients, the surgeon removes the brain tissue from which seizures originate. In others, the seizure-producing tissue may be treated with minimally invasive ablation, or pathways involved in seizure spread may be disconnected.
Some procedures aim primarily for seizure freedom, while others are intended to reduce seizure frequency or severity when removing the seizure focus is not considered safe.
The major approaches include resection, ablation, disconnection, and neuromodulation.
What Are the Types of Epilepsy Surgery?
1. Resective Surgery
Resective surgery removes the area of brain tissue responsible for generating seizures.
It may be considered when the seizure focus can be accurately identified and removed without causing an unacceptable neurological deficit.
Examples include:
- Lesionectomy: removal of a specific abnormal area or lesion in the brain that is responsible for seizures.
- Focal cortical resection: removal of a defined area of the cerebral cortex from which seizures originate.
- Temporal-lobe surgery: surgery targeting a seizure-producing area in the temporal lobe, a region involved in functions such as memory and language.
- Other tailored resections designed around the individual’s seizure focus and functional anatomy.
Resective procedures are generally intended to achieve seizure freedom.
2. Laser or Thermal Ablation
Ablation treats the seizure-producing tissue without requiring the same type of open brain resection.
Depending on the technology and clinical setting, thermal energy may be used to destroy the targeted tissue.
These minimally invasive approaches can be useful in selected patients, particularly when a small, well-defined seizure focus can be safely targeted.
3. Disconnection Surgery
Disconnection procedures interrupt pathways through which seizures spread.
They may be considered when the seizure-producing abnormality involves a large or functionally important area where complete removal would carry an unacceptable risk.
Examples include:
- Corpus callosotomy: surgery that partially or completely disconnects the corpus callosum, the major bundle of nerve fibres connecting the brain’s two hemispheres. It is mainly used to reduce the spread of certain severe seizures, including some seizures that cause sudden falls.
- Hemispherotomy or hemispheric disconnection: a procedure that disconnects most or all of one abnormal brain hemisphere from the rest of the brain without necessarily removing the entire hemisphere. It may be considered in children with severe epilepsy arising predominantly from one hemisphere.
- Other tailored disconnection procedures: operations designed to interrupt specific pathways through which seizures spread while preserving as much healthy brain tissue and function as possible.
These operations may aim to reduce the frequency or severity of disabling seizures rather than guarantee complete seizure freedom.
4. Neuromodulation
Neuromodulation uses an implanted device to influence abnormal electrical activity in the brain or associated neural pathways.
Options may include:
- Vagus nerve stimulation (VNS): an implanted device sends electrical signals to the vagus nerve, which carries signals between the brain and other parts of the body, to help reduce seizure activity.
- Responsive neurostimulation (RNS): a device monitors brain activity and delivers stimulation when abnormal electrical patterns associated with seizures are detected. It may be considered in selected patients where the seizure focus cannot safely be removed.
- Deep brain stimulation (DBS): an implanted device that delivers electrical stimulation to specific brain structures involved in seizure networks.
Neuromodulation is generally considered when resection or ablation is not suitable, or when the treatment goal is seizure reduction rather than removal of a single safely resectable seizure focus.
What Is the Success Rate of Epilepsy Surgery in India?
There is no single success rate for epilepsy surgery in India.
Outcomes depend on factors such as:
- type of epilepsy
- location of the seizure focus
- underlying cause
- type of procedure
- completeness of treatment of the seizure-producing region
- results of presurgical testing
- duration and severity of epilepsy
- individual neurological factors
However, Indian studies demonstrate that substantial seizure control is achievable in appropriately selected patients.
Evidence from Indian Adults With Temporal-Lobe Epilepsy
A cohort study of 288 adults with drug-resistant temporal-lobe epilepsy reported that 73% were seizure-free at last follow-up, while 82% had a favourable Engel outcome. Follow-up ranged from 1 to 10.3 years.
Evidence From an Indian Tertiary Epilepsy Centre
Another Indian study involving 51 patients undergoing electrocorticography-guided epilepsy surgery reported that 43 patients (84.31%) were completely seizure-free, classified as Engel Class I, at a mean follow-up of 33 months.
Electrocorticography is a method of recording electrical activity directly from the surface of the brain using electrodes placed during surgery or an invasive monitoring procedure.
The patients had selected structural causes including mesial temporal sclerosis, focal cortical dysplasia and tumours.
Evidence From Indian Children
As noted above, a study of 242 children undergoing epilepsy surgery reported an 81.38% Engel Class I outcome after definitive surgery, with outcomes varying according to the surgical approach.
These studies provide useful India-specific evidence, but their results should not be averaged into one universal “epilepsy surgery success rate.” The populations, epilepsy types, procedures, and outcome definitions differ.
Can Epilepsy Surgery Stop Seizures Completely?
It can, in appropriately selected patients, but seizure freedom cannot be guaranteed.
The likelihood depends heavily on whether the seizure-producing region can be accurately identified and safely treated.
For example, an Indian study of extratemporal drug-resistant epilepsy found that 71 of 285 evaluated patients underwent resective surgery, and 73.2% of the surgical group were seizure-free compared with 7.7% of those who were not selected for surgery. The study also illustrates why patient selection matters: factors such as MRI findings, seizure localisation and proximity to eloquent brain areas influenced whether surgery was possible.
Eloquent brain areas are regions responsible for important functions such as speech, movement, sensation or vision, where damage could cause significant neurological problems.
Is Epilepsy Surgery Safe?
Epilepsy surgery can be performed safely in appropriately selected patients, but it is still major brain surgery and carries potential risks.
The risks depend on the location and type of procedure.
Potential complications may include:
- bleeding
- infection
- swelling
- seizures
- weakness or sensory changes
- speech or language difficulties
- memory or cognitive changes
- visual-field changes
- anaesthesia-related complications
- other neurological deficits
The risk is particularly influenced by whether the planned treatment is close to brain regions responsible for important functions.
What Is the Recovery Time After Epilepsy Surgery?
Recovery varies considerably depending on the type of epilepsy surgery, the area treated, and the person’s overall health.
Some procedures require a longer hospital stay and recovery period than others.
During recovery, the medical team may monitor:
- seizure activity
- neurological function
- wound healing
- headaches or other postoperative symptoms
- movement and strength
- speech and language
- memory and cognition
- medication response
Returning to normal activities is usually gradual. Work, school, driving, and exercise may each have different timelines depending on the person’s recovery and medical advice.
Follow-up is important because seizure control is assessed over time rather than immediately after leaving the hospital.
Will I Need Anti-Seizure Medication After Epilepsy Surgery?
Many people continue anti-seizure medication for some time after surgery, even if seizures stop.
Whether and when medicines can be reduced depends on factors such as:
- seizure control after surgery
- type of epilepsy
- surgical procedure
- EEG findings
- underlying cause
- the treating team’s assessment
Medication should not be stopped or reduced without medical supervision.
In some carefully selected patients who remain seizure-free, a specialist may eventually consider reducing medication. The timing and suitability of this decision are individual.

When May Epilepsy Surgery Not Be Recommended?
Epilepsy surgery may not be recommended when the risks outweigh the expected benefits or when the seizure focus cannot be adequately identified or safely treated.
Reasons may include:
- seizures arising from multiple or poorly localised areas
- a seizure focus located in an area where treatment could cause unacceptable neurological deficits
- insufficient agreement between presurgical investigations
- inability to identify a surgically treatable target
- medical or other factors that substantially increase surgical risk
Importantly, not being a candidate for resective surgery does not mean there are no treatment options.
Depending on the person’s epilepsy, doctors may consider medication optimisation, dietary therapy in selected cases, neuromodulation, ablation or palliative procedures.
The purpose of a surgical evaluation is therefore broader than simply deciding “surgery or no surgery.” The evaluation can also clarify the diagnosis and help determine the most appropriate treatment pathway.
What Should You Ask Before Epilepsy Surgery?
Before making a decision, patients and families can ask the epilepsy team:
- What type of epilepsy do I have?
- Where do my seizures appear to start?
- Which tests are still needed before surgery?
- Is the seizure focus clearly localised?
- What type of epilepsy surgery is being considered?
- Is the goal seizure freedom or seizure reduction?
- What are the expected benefits in my specific case?
- What are the major risks?
- What neurological functions could be affected?
- Will I need anti-seizure medicines after surgery?
- How long might recovery take?
- What happens if surgery does not control my seizures?
- Are there non-surgical or less-invasive alternatives?
- What will the total treatment cost include?
A second opinion from another specialised epilepsy centre may also be reasonable when the proposed procedure is complex or when the patient or family wants another assessment of the risks and benefits.
Start your healthcare journey by choosing to Find hospital and fund your treatment today.
Conclusion
Epilepsy surgery can offer significant seizure control, and in appropriately selected patients it may provide long-term seizure freedom. However, surgery is not automatically appropriate for everyone with drug-resistant epilepsy. A detailed presurgical evaluation is needed to identify where seizures begin, determine whether that region can be treated safely, and select the most suitable procedure. Indian studies have reported favourable outcomes in selected adult and paediatric populations, but individual results vary. If seizures remain uncontrolled despite appropriate medicines, discussing referral to a specialised epilepsy centre can be an important next step.

FAQs
Epilepsy surgery refers to procedures used to reduce or stop seizures by removing, destroying or disconnecting seizure-producing brain tissue, or by using neuromodulation to reduce abnormal seizure activity.
People with drug-resistant epilepsy may be considered for surgical evaluation, particularly when investigations can identify a seizure focus that can be treated safely. Eligibility is determined after a detailed presurgical assessment rather than from the diagnosis alone.
Epilepsy surgery can result in long-term seizure freedom for some appropriately selected patients, but it does not guarantee a cure. Outcomes depend on the type of epilepsy, seizure focus, procedure, and individual factors.
Presurgical evaluation commonly includes clinical assessment, long-term video EEG, high-resolution MRI, and neuropsychological testing. Depending on the case, doctors may also use PET, SPECT, functional mapping, or intracranial EEG.
The main approaches include resective surgery, ablation, disconnection procedures, and neuromodulation. The appropriate option depends on where seizures originate and whether that area can be treated safely.
Yes. Children with drug-resistant epilepsy may undergo surgery when a specialist evaluation shows that it is appropriate. Early evaluation can be important because prolonged uncontrolled seizures may affect development and quality of life.
Possibly. Many patients continue anti-seizure medicines after surgery. Whether medication can eventually be reduced depends on seizure control and individual clinical factors.







